kelIsya

Daisypath Wedding tickers
Showing posts with label surgery. Show all posts

Thursday, August 25, 2011

surgery exam yr 5


Examiner: Mr Ramzi
Wad 7C
For the history, CQ should be in patients own word and use medical terms in HOPI. Eg: patient complained  of blood in the urine for 7 years. HOPI hematuria was associated with severe flank pain. Stenting and ESWL was done 10x and 3 operation was perform however the symptoms did not improved.
For examination, as patient is day 1 post op-PCNL, so patient refused to lie down.
Patient had nephrostomy tube at the back on the left side, 10 cm from the spinous process and 15 cm infrascapular. The NT tube drain 1500ml hematuria and cast seen in the tube. Otherwise, no pus no stone in the urinary bag.
My impression is, patient has left renal stone and was treated with PCNL.
DISCUSSION
Q: why you said it is renal stone not ureteric or bladder stone
A: history of flank pain and hematuria, history of ESWL and had neprostomy tube.
Q: what is the risk factor for renal stone?
A:1) high oxalate diet. Eg:chocolate milk, black tea, soy, yogurt
    2)dehydration
   3) stasis in infection or tumor.
   4)urinary ph: urate and oxalate in acidic urine and struvite and phosphate in alkaline urine.
   5)endocrine abnormality-eg: hyperPTHàhypercalcemia.
   6)metabolite imbalance: hyperuricemia à uric acid stone.
Q: if there is a male presented with flank pain and hematuria, how you will investigate??
A: specific investigation, I would like to perform KUB x-ray which is 90% sensitive for the renal stone
Q: if you cannot see stone on x-ray, what are other modalities:
A: ultrasounds. Ultrasound can pick up uric acid stone and xanthine stone.
    IVU
Q: you had treated this patient with PCNL. What advice you can give to the patient to prevent recurrent.
A: 1) I will investigate if for the uric acid level, PTH and calcium level to exclude endocrine and metabolite problem and treat accordingly if present.
     2)dietary recommendation- I would advice patient to drink adequate water, drink more citrus juice and avoid high oxalate diet, high protein diet and high dose of vit C
Q: what is the complication if you do not remove the stone.
A:The stone can lead to obstruction àinfection. Obstruction also can lead to hydronephrosis and patient later will developed renal failure.
Q: what will happened of this patient develop renal failure (this question is little bit tricky ^_^)
A: as long as the right kidney is normal, patient would not develop any sign or symptoms.
Q: what is the investigation specifically to look for renal damage. Not blood investigation.
A: renal scan. Scincitograpy.
Ok.. lets moved to the short case J
Q: examine the abdomen
A: abdomen is distended at the lower part below the umbilicus……………on deep palpation there is a mass palpable at the pelvic are. The mass irregular surface, hard in consistency and ill-defined margin. No pulse palpable   I cannot go below the mass but can go above it. The mass is fix. On percussion the mass is dull.
Q: how to differentiate between pelvic or abdominal mass?
A: can go above it or below it. As the patient, I cannot go below it, so likely the mass is pelvic origin.
Q: how to percuss pelvic mass
A: from the xiphisternum to the symp pubis.
Q: generally, how the patient look? And what is your diagnosis
A: generally, patient is cachexic and lethargic and the conjunctiva and oral mucosa is pale. I think patient hand pelvic cancer which might be bladder ca, ovarian ca or uterine ca.

SEKIAN.selamat berpuasa and selamat beramal di akhir ramadhan. Semoga bertemu lagi pada ramadhan akan datang and kite semua menjadi insan yang lebih baik and berkhidmat kepada masyarakat. insyaAllah semua orang jadi doctor pada ramadhan akan dtg, last word, kalo ada kekurangan dalam script ni jangan segan2 betulkan atau tambah. Hope all of us will benefit from it.



Saturday, August 13, 2011

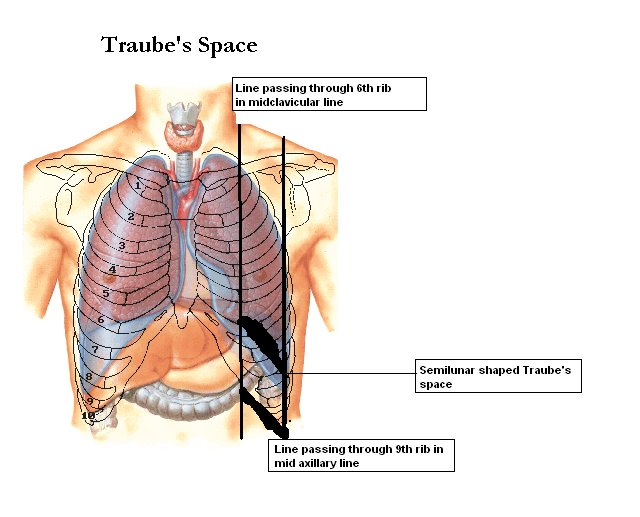
Traube's space notes


Gastroenterology:Traube's space


Surface Markings

1. Draw two vertical lines one passing through the 6th rib in the midclavicular line and the next passing through the 9th rib in midaxillary lines.

2. Now draw a smooth curving line with convexity upwards ftom the sixth rib in midclavicular line to 9th rib in midaxillary line.

3.Draw another straight line passing through the costal margin from 6th rib to 9th rib.

All these boundaries enclose a near semilunar space called Traubes space.

Anatomical boundaries are:

1. Right : Lateral margin of left lobe of liver.
2. Left : Spleen.
3. Superior : Resonance of lung.
4. Inferior : Costal margin.

Contents

1. Fundus of stomach (Hence percussion of Traubes area normally gives Tympanitic resonance).
2. Costo-phrenic recess of left pleura devoid of lungs.

Causes of obliteration of Traubes space:
1. Full stomach.
2. Left sided Pleural effusion.
3.Splenomegaly.
4. Enlargment ofleft lobe of liver due to any etiology.
5. Dextrocardia.
6. Proloiferative growth in fundus of stomach.

Note: A left lung mass lesion/consolidation alone never produces impairment as lung is not extending to traube's space.

traubes-space on clinicalmedicineupdate

Sunday, July 17, 2011

abdominal pain

presenter: isya
dr Mular

52 yr old chinese gentleman was admitted on 11/7/11 at 4B

problem lists:
1)abdominal pain 3/52
3 weeks duration of progressingly worsening and fluctuating squeezing pain at the upper abdomen.
the pain disturbing patient sleep with no aggravating and relieving factor.
3 days PTA, loose stools and tenesmus
associted with LOA & LOW and progressively become lethargy.
no nausea, no vomiting, no PR bleed, no jaundice, no pale colored stool

2)low grade fever 3/52
intermittent
fever at evening and night,relieved by PCM

no hx of blood transfusion, no tatto

history of multiple sexual partners, and sexual partner with multiple sexual partner

had color vision deficit, red-green, otherwise no DM, no HPT no Asthma.

past surgical/drug/allergy-nil

past family hx: both parents die due to cx of DM and HPT.no fhx of malignancy

social hx: married with 3 children, A&W
smoke for 60 pack-year
consume alcohol for 20 yrs(2 bottle of beerx2/week)
working as mechanic with income of 2k-3k

0/E
pt well, pink orientated to TPP, no in respiratory difficulty, not complaining any pain

vital signs normal

abdominal examination:
distended epigastric and periumbilical
soft abdomen, tenderness over the epigastric, RHC,r.lumbar and RIF.
firm liver mass,6cm from costal margin, smooth surface with prominent hard nodule at the epigastric region, tender, no bruit
liver span:16cm

spleen, kidney, not palpable.

no ascites

normal bowel sound

refused for DRE

CVS, respi-normal

Differential dx:

1: 2ndary mets to the liver from gi
more common than primary
hx of loa,low
liver mass

2. primary liver ca
loa, low
liver mets
risk for hepatitis

3.pyogenic liver abscess
tender liver mass.

4.hemangioma of the liver

5. benign liver tumor

6. liver cyst

ix:

blood ix:
1. fbc tro inflammation/infection
2. LFT
3. CEA
4. AFP

imaging
1.abdominal u/s
2. CT scan

diagnosis
1. liver mets fr GI malignancy
2. diverticulis

Friday, June 24, 2011

surgery year 4 end of posting exam part 1


today is the last day of my fourth year exam.. and i want to share the case that i got..
hope we learn something from this post.

Long case
63 year old Malay male presented with 1 day history of diarrhoea and vomiting.
he is asthmatic since 15 years ago otherwise was previously well.
he had diarrhoea, about 20-25 on that day, watery and yellowish in color, no blood or mucus, associated with abdominal pain.
he had the vomiting after the episodes of diarrhoea, post-meal vomiting with gastric content,no blood about 20 times PTA. he become lethargic and drowsy and was brought by his family member to ED.
associated symptoms, fever,palpitation and SOB on that day, LOA and LOW(3-4kg) for 1 months duration.
there is history of eating outside but no other family member had similar problem.
also had voiding symptoms(LUTS)
otherwise, denied any change in bowel habit, no PR bleed.
no DM/hpt/ptb. he take t.ventolin for the asthma and controlled
had been admitted previously for 6 days in HS after had SOB- treated as asthma and dengue fever.
no allergy
no family hx of malignancy or inflammatory bowel disease.
he was an ex-chronic smoker (42 yrs X 20) stop about 1 year ago.

o/e:
well/not complain in pain/very cooperative
conscious alert to TPP, thin, hydration status good
dry and scally skin over elbow and below, ankle and below, face extended to the neck.
not pale or jaundice
had white patch on the tongue but pt claim it was painless.
no palpable cervical, supraclavicular LNs. no pitting edema.

abdominal examination
the abdomen was not distended and move freely with respiration.
there was a stoma bag at the left iliac fossa with solid stool, no mucus/blood/pus
the was an midline incision measuring 8cm from below extending up to hypochondriac region.
there was also 2 scar at the anterior axillary line, likely to be scar for the drainage of the peritoneum( at the right iliac fossa) and from the chest tube(at the safe area for the chest tube insertion)
the abdomen was soft, non tender, no mass palpable.
no hepatosplenomegaly, the kidney was not ballotable.

posterior abdomen
no abnormality

i'm no able to auscultate as the doctor came earlier, the doctor suppose to come by 9.50 but she was there at at 9.30.
i was not able to do auscultation, do the PR and polish my history as well as  the pe. and the most important,to think about the differential diagnosis, investigation and management that i was suppose to prepare before the examiner come.

so i just blurt out during the exam..

the discussions were:
1. what is your differential diagnosis?
2. how to investigate for your diagnosis?
3. if there is mass at recto-sigmoid junction found during colonoscopy, how you will proceed?
4. what is the type of the benign lesion - polyp - type of polyp?
5. if the lesion is dysplasia, how do you manage the patient?
6. what is the complication of the surgery?
7. how to prevent DVT
8. how do you stage colorectal ca.

if will post the proper answer in the next entry ;) just give yourself a break to think about the question

p/s: this is a very common case we are going to encounter in surgical posting.. goodluck.

testing ;)

lalala